
Friday, November 20, 2026



News and Views from the Global South
Opinion
The Future of Surgery in Africa
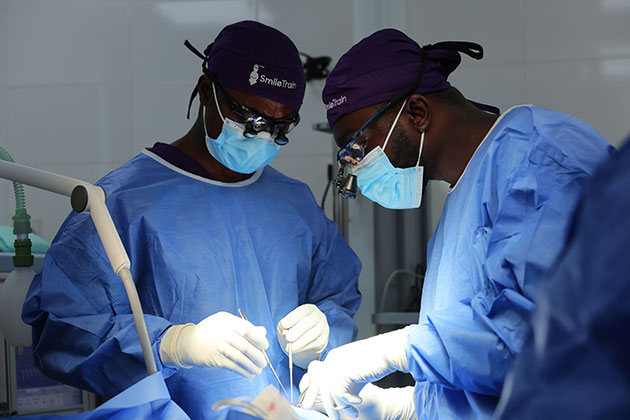
Two surgeons perform a surgery on their patient, Miracle, in the operating room at the National Cleft Care Center in Kumasi, Ghana. Credit: Smile Train
- In too many communities across our continent, a baby born with a cleft lip or palate is met with fear instead of a plan. Some families are told the child is cursed. Some mothers are even forced out of their homes. Yet a cleft is one of the most common and treatable conditions in medicine. A safe operation, done early, lets a child eat, speak and grow up with a bright future.
So when that child goes untreated, the problem is not biology. It is a sign that something is missing: the surgeon, the anesthetist, the nurse, the working operating room, the reliable electricity, the road to the right hospital. In this way, cleft is a bellwether for the strength of health systems overall.
Across sub-Saharan Africa, 93% of people cannot get safe, affordable surgery and anaesthesia when they need it, compared with under 4% in wealthier regions. In Ethiopia alone, roughly five million needed operations go undone each year.
From November 19 to 21, health leaders, surgeons, researchers and partners from across Africa will meet in Addis Ababa for the fourth Pan-African Surgical Healthcare Forum (PASHeF). Its goal is ambitious and overdue: a continental action framework for surgical care.
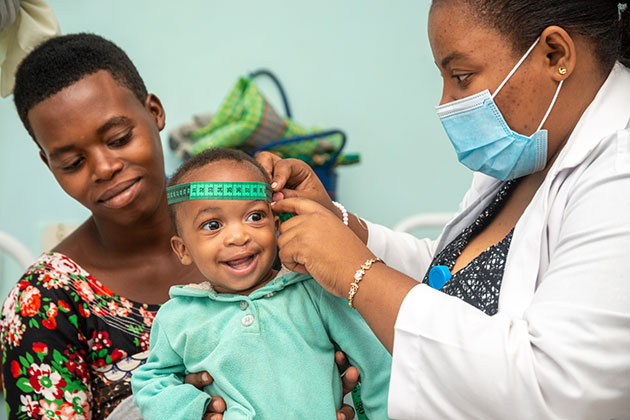
A doctor measures the nutritional development of a cleft patient at a hospital in Tanzania. Credit: Smile Train
Surgery is health care, not a luxury
For decades, surgery was treated as something that could wait until vaccines, bed nets, and clinics were in place. As a result of that longstanding underinvestment, an estimated 93 million Africans need surgical care every year, yet only about 5% receive it.
The World Health Assembly has recognized emergency and essential surgery and anaesthesia as a core part of universal health coverage. Invest in surgical capability, and you strengthen the whole hospital’s ability to deliver across a wide range of needs: emergency care, safe childbirth, trauma, cancer.
Ethiopia took that commitment seriously. In 2016, it became one of the first countries to write a national surgical plan, Saving Lives Through Safe Surgery (SaLTS).
What we have learned
The challenges were familiar: leadership changes, too little reliable data, and no dedicated budget to reach the whole country. A study of the plan’s rollout found that government ownership was the most important ingredient for success.
Experience from outside government points the same way. Over 25 years, Smile Train’s approach has been to support local teams working inside national systems rather than fly in visiting surgeons. Those teams have now performed nearly 250,000 free cleft surgeries across Africa, more than 46,000 of them in Ethiopia since 2007. Three lessons stand out.
Build with government, not beside it. In Kumasi, Ghana, the Ministry of Health, Komfo Anokye Teaching Hospital and the Ghana Cleft Foundation co-created the National Cleft Care Center. Government clinicians staff it, and cleft surgery there has gone from one day a week to every day.
Train together. When Africa’s surgical colleges agreed on a single cleft surgery curriculum, it spread across the continent in English, French and Portuguese.
Fix the basics. A well-equipped theatre is useless in a blackout, yet families are still asked to bring diesel for the generator. Solar systems installed with Kids Operating Room now power more than 85 children’s operating theatres in 28 countries, three of which are public hospitals in Ethiopia.
Together they show what works: government ownership, a local workforce, data that is tracked, and infrastructure that actually runs.
What the framework must do
The Addis Ababa forum should commit African governments to four key things:
- • Put surgery in the budget. Plans without money stall. Finance ministries belong at the table from day one, and domestic funding should anchor what partners add.
• Train and keep the workforce. Shared regional curricula, scholarships, and alumni networks can prepare young specialists to replace an aging generation of surgeons.
• Count what matters. Every country should track surgical access and outcomes in its national health data, as Ethiopia now does with its registry.
• Start with families. Ending the stigma around conditions like cleft takes midwives, community health workers, religious leaders and traditional rulers, not just doctors.
A year ago, the African Union and Africa CDC unveiled the Health Security and Sovereignty Agenda, a blueprint for African countries to build stronger health institutions, finance health from their own resources and grow local capacity. Surgery is where that ambition is tested: a country that can staff, equip, power and pay for its own operating theatres can meet its people’s needs on its own terms.
These steps can have a meaningful impact now and for future generations. As long as children are born, some will be born with a cleft. A poor child in a rural district deserves the same chance of a safe operation as an affluent child in a capital city. This week in Addis Ababa, Africa’s leaders can commit to making that happen.
Nkeiruka Obi is Vice President and Regional Director, Africa, Smile Train
IPS UN Bureau


 Print
|




